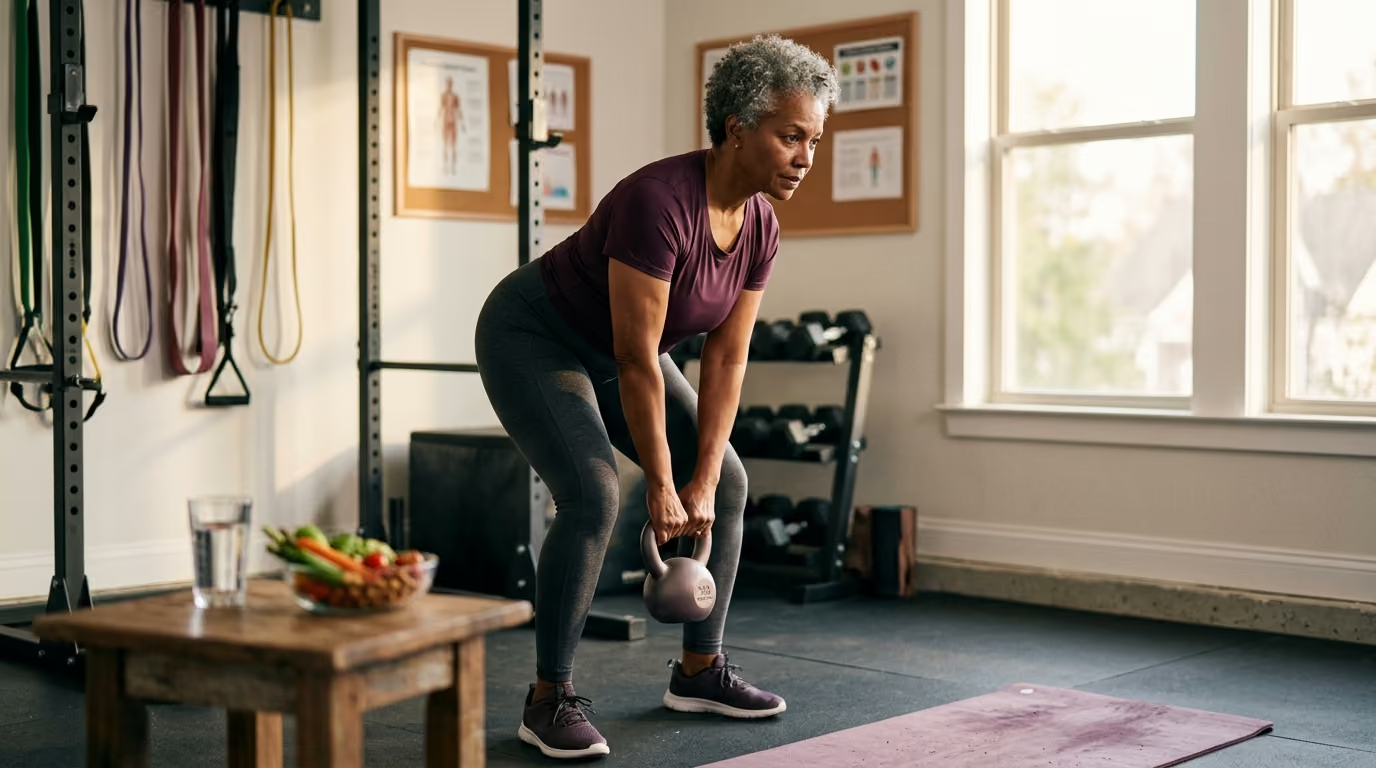

Sustainable strength, healthy bone density, and metabolic balance after menopause require targeted daily protein, progressive resistance training, and key micronutrient adjustments.





Nutrition after menopause is not a crash diet protocol or an anti-aging checklist. It is a systematic physiological approach to supporting bone mineral density, lean muscle mass, cardiovascular health and daily functional vitality. For decades, midlife nutrition has been framed almost exclusively as a battle against the bathroom scale. That framing is incomplete and often counterproductive. When menstruation ends, hormonal shifts alter how your body handles energy, builds muscle, retains minerals and regulates blood lipids.
Navigating this stage requires moving away from severe caloric restriction and moving toward nutrient density, strength preservation and cardiometabolic protection. A well-constructed dietary approach respects the biological changes of the postmenopausal years without treating normal aging as a medical failure. This comprehensive guide covers the physiological realities of midlife hormonal change, precise protein requirements, bone preservation strategies, iron adjustments and sustainable meal frameworks. You will learn how to feed your body for decades of independence, energy and physical resilience.
Menopause is clinically defined as the point in time occurring 12 consecutive months after a woman's final menstrual period. The years leading up to this point represent perimenopause, while the subsequent stage is postmenopause. During this transition, circulating levels of estradiol decline significantly. This hormonal shift directly influences where your body stores fat, how efficiently it uses fuel and how rapidly muscle tissue breaks down.
Research summarized by the North American Menopause Society indicates that the menopause transition is characterized by an increase in total body fat and a decrease in lean tissue mass. On average, midlife women gain roughly 1.5 pounds per year across this period. This average rate varies widely based on physical activity, genetics and sleep quality. Weight trajectories tend to stabilize approximately two years after the final menstrual period.
The primary change during this time is not merely scale weight, but tissue redistribution. Estrogen promotes fat storage in the hips, thighs and subcutaneous depots. When estrogen levels drop, fat storage shifts toward an abdominal, visceral pattern. Visceral fat surrounds internal organs and is metabolically active, releasing inflammatory cytokines that can alter insulin sensitivity and lipid balance. This shift can occur independently of total body weight changes.
Resting metabolic rate often decreases during midlife. This change happens largely because skeletal muscle tissue, which requires significant daily energy to maintain, naturally declines with age and lower estrogen levels. The solution to a lower metabolic rate is not eating progressively less food each year. Severe caloric restriction accelerates the loss of lean muscle, which further depresses your metabolic rate. Instead, postmenopausal nutrition focuses on preserving functional tissue through adequate fueling, high nutrient density and progressive strength training.
Understanding these changes allows you to choose an appropriate metabolic objective. Depending on your current health status, your goal may be weight stability, body recomposition or moderate fat loss.
Maintaining your current body weight while improving strength, cardiovascular markers and energy levels. This approach is ideal when your blood pressure, glucose and cholesterol are within healthy ranges.
Preserving a stable scale weight while simultaneously building skeletal muscle and reducing visceral fat stores. Recomposition improves functional capacity and metabolic flexibility without requiring a large caloric deficit.
Creating a gentle, sustainable energy reduction when excess adipose tissue compromises mobility, joint comfort or cardiovascular health. This strategy prioritizes high protein intake and resistance training to spare lean tissue while body fat decreases.
You can learn more about managing these physiological shifts through our dedicated resources on strength, body composition and metabolism.
Skeletal muscle is the metabolic engine of the human body. As estrogen declines, women become more susceptible to sarcopenia, which is the age-related loss of muscle mass and physical function. Women are also vulnerable to dynapenia, which is the loss of muscular strength independent of muscle size. Protecting both muscle mass and strength is critical for lifelong balance, mobility and metabolic health.
The conventional Recommended Dietary Allowance for adult protein intake is 0.8 grams per kilogram of body weight per day. This baseline was established primarily to prevent deficiency in sedentary adults. Multiple menopause-focused nutritional reviews suggest that postmenopausal women benefit from higher daily protein targets, often ranging from 1.0 to 1.2 grams per kilogram of body weight. Some researchers propose ranges up to 1.1 to 1.5 grams per kilogram for active women engaged in heavy training.
Higher protein intakes are not automatically superior in every context. A randomized trial examining postmenopausal women participating in resistance exercise found that consuming approximately 1.2 grams per kilogram per day did not produce greater lean mass gains than consuming 0.8 grams per kilogram. Training consistency, total daily energy intake and baseline diet heavily influence muscular adaptations. The optimal target is one that supports recovery and strength without causing digestive distress or displacing other nutrient-dense foods.
Protein distribution throughout the day provides steady amino acid availability for muscle repair. A practical approach divides protein intake across two to four meals rather than concentrating it all in the evening. However, a randomized clinical trial in postmenopausal women showed that specific protein timing around workouts did not significantly alter lean mass or strength gains when total daily intake was sufficient. Meeting your daily protein total consistently matters far more than following rigid nutritional timing rules.
A wide variety of whole foods supply high-quality amino acids:
Plant-based diets can fully satisfy midlife protein requirements. Combining legumes, whole grains, seeds and soy foods ensures a diverse amino acid profile across the day.
Protein powders, such as whey isolate or pea-rice blends, can serve as convenient supplementary options when appetite is low or schedules are demanding. A meta-analysis examining whey protein supplementation in postmenopausal women demonstrated modest improvements in upper-body strength and lower-limb lean mass when combined with resistance exercise. Whey supplementation without resistance training did not produce meaningful improvements in strength or lean tissue. Supplements should be viewed as practical tools rather than mandatory solutions.
Nutrition provides the essential building blocks for tissue repair, but mechanical tension is the required signal for muscle and bone adaptation. Without physical resistance, excess dietary protein cannot stimulate new muscle protein synthesis effectively. Dieting without strength training causes a significant portion of weight loss to come directly from skeletal muscle and bone tissue.
A systematic review across 43 studies involving postmenopausal and older women confirmed that resistance training programs produce small-to-moderate increases in lean body mass. Exercise training consistently improves muscle strength and physical capacity compared with sedentary routines. Programs incorporating structured resistance exercise approximately three times per week showed the most robust improvements in functional performance.
Resistance training must follow the principle of progressive overload. This means gradually increasing mechanical challenge over time by adding weight, performing more repetitions or improving movement control. A balanced weekly program focuses on functional multi-joint movements:
Strengthens quadriceps, gluteal muscles and knee stability. Useful for maintaining the ability to rise easily from chairs and low surfaces.
Develops the posterior chain, including the hamstrings, glutes and spinal erectors. Essential for lifting heavy household objects safely from the floor.
Builds chest, shoulder, upper back and arm strength. Supports postural alignment, shoulder joint resilience and pulling tasks.
Involves walking while holding weights at your sides or chest. Builds grip strength, core stability and total-body coordination.
Daily walking provides exceptional cardiovascular and mental health benefits, but it does not provide the compressive force needed to build bone density or preserve upper-body lean mass. Dedicated strength training must form the foundation of any midlife physical routine. You can review our comprehensive articles on midlife nutrition and weight management to align your daily meals with your training schedule.
Bone mineral density declines rapidly during the first several years following menopause due to the loss of estrogen's protective effect on bone remodeling cells. Osteoclasts break down old bone faster than osteoblasts can form new matrix. Protecting the skeleton requires a combination of adequate micronutrients, sufficient energy intake and weight-bearing exercise.
The Recommended Dietary Allowance for calcium increases from 1,000 milligrams daily for younger adult women to 1,200 milligrams daily for women aged 51 and older. The International Osteoporosis Foundation similarly recommends 1,200 milligrams per day for postmenopausal populations. This mineral is best obtained through whole dietary sources rather than large single-dose supplements.
Dietary calcium is absorbed efficiently when distributed across meals throughout the day. Dairy products, fortified plant milks, calcium-set tofu and small bone-in fish provide high concentrations of bioavailable calcium. Low-oxalate leafy greens like kale, collard greens and bok choy allow for good mineral absorption. Spinach contains substantial calcium, but its high oxalic acid content binds to the mineral and prevents significant absorption in the digestive tract.
Vitamin D facilitates intestinal calcium absorption and supports muscle function. The National Academy of Medicine recommends 600 International Units of vitamin D daily for women aged 51 to 70, increasing to 800 International Units daily after age 70. Serum vitamin D levels vary based on sun exposure, geographical latitude, skin pigmentation, body composition and digestive health. Periodic blood testing helps determine whether targeted supplementation is necessary.
A common misconception is that taking high-dose calcium and vitamin D supplements will automatically prevent bone fractures. The U.S. Preventive Services Task Force recommends against daily supplementation with 400 International Units or less of vitamin D combined with 1,000 milligrams or less of calcium for the primary prevention of fractures in community-dwelling postmenopausal women without osteoporosis. Routine supplementation in healthy individuals does not replace the powerful structural stimulus of progressive resistance exercise and fall-prevention training.
Bone density is intimately linked to total body composition. A longitudinal study demonstrated that each standard deviation increment in lean mass loss was associated with a 63 percent greater fracture hazard following the menopausal transition. Fat mass gain was associated with a 28 percent increased fracture hazard. Protecting your bones requires preserving functional muscle mass through balanced nutrition and strength training, rather than relying solely on mineral pills.
During the reproductive years, monthly menstrual blood loss represents the primary route of iron elimination from the female body. Because women lose red blood cells regularly, the Recommended Dietary Allowance for premenopausal adult women is 18 milligrams of iron per day. Once menstruation permanently ceases, iron requirements decline substantially.
For women aged 51 and older who are fully postmenopausal, the Recommended Dietary Allowance drops to 8 milligrams daily. Continuing to take high-dose iron supplements or multis containing reproductive-age iron levels after periods stop can lead to unnecessary iron accumulation in bodily tissues. The human body has no active physiological mechanism to excrete excess iron beyond normal cellular shedding.
Dietary iron occurs in two forms: heme iron, found in animal meats and seafood, and non-heme iron, found in plant foods such as beans, lentils, whole grains, nuts and dark leafy greens. Heme iron is absorbed efficiently by the gut, while non-heme iron absorption depends on accompanying dietary factors. Consuming vitamin-C-rich foods alongside plant-based iron sources enhances non-heme absorption. Drinking coffee or black tea directly with meals can inhibit non-heme iron uptake due to the presence of polyphenols and tannins.
This nutritional transition presents two frequent errors that require attention:
Many women continue taking multivitamin formulations designed for menstruating adults long after their cycles have ended. Unless a physician has documented iron deficiency, postmenopausal women should choose iron-free multivitamin formulas.
While iron requirements drop after menopause, deficiency can still occur. Gastrointestinal blood loss, celiac disease, malabsorption disorders or poor dietary intake can cause anemia. Any unexplained iron deficiency or fatigue in a postmenopausal woman requires medical investigation rather than self-directed supplementation.
If you are currently navigating fluctuating cycles, you can review our educational guides on the perimenopause and hormonal transition for cycle-specific nutritional recommendations.
Estrogen plays a protective role in the female cardiovascular system by promoting nitric oxide production, supporting arterial elasticity and maintaining favorable lipid profiles. Following menopause, women often experience an increase in low-density lipoprotein cholesterol, a decrease in high-density lipoprotein cholesterol and a rise in systemic blood pressure. Nutrition plays a primary role in stabilizing these cardiometabolic parameters.
Rather than focusing on single isolated foods, long-term cardiovascular resilience is best achieved through a coherent dietary pattern. A Mediterranean-style eating framework consistently demonstrates powerful protective effects in midlife and older adults. This dietary pattern emphasizes whole plant foods, healthy fats and lean protein sources while minimizing ultra-processed items.
Dietary fat quality is significantly more important than total fat quantity. Replacing saturated fats from fatty meats, butter and tropical oils with monounsaturated and polyunsaturated fats improves lipid markers and arterial function. Utilizing extra-virgin olive oil as your primary culinary fat, eating avocados and including walnuts or chia seeds daily supports endothelial health.
Soluble and insoluble dietary fiber serves multiple metabolic roles. Fiber slows gastric emptying, blunts postprandial glucose spikes, improves insulin sensitivity and assists in clearing cholesterol from the bloodstream. Aim for 25 to 35 grams of total dietary fiber daily. Legumes, oats, barley, apples, berries, flaxseeds and cruciferous vegetables are exceptional sources. Increase your fiber intake gradually across several weeks while consuming adequate water to avoid abdominal cramping or bloating.
Blood pressure regulation requires thoughtful attention to sodium and potassium balance. The Dietary Guidelines for Americans recommend limiting sodium intake to less than 2,300 milligrams per day. The majority of dietary sodium comes from packaged foods, restaurant meals, commercial sauces, processed deli meats and industrial breads rather than the home salt shaker. Pairing sodium moderation with potassium-rich foods like potatoes, winter squash, leafy greens, yogurt and bananas helps maintain healthy vascular tone.
Alcohol consumption warrants careful self-reflection in the postmenopausal years. The Dietary Guidelines state that adults who choose to drink should limit intake to one standard drink or less per day for women. Alcohol can disrupt restorative sleep architecture, trigger vasomotor flushing, elevate resting blood pressure and impair nighttime glucose control. Reducing or eliminating alcohol intake often leads to immediate improvements in energy and sleep continuity.
Vasomotor symptoms, including hot flashes and night sweats, affect up to 80 percent of women during the menopause transition and can persist for years into postmenopause. These symptoms originate in the hypothalamus, where declining estrogen levels alter thermoregulatory control. While dietary interventions cannot fully replace medical therapies for severe vasomotor symptoms, certain nutritional choices can help moderate symptom frequency and severity.
Soy foods contain naturally occurring isoflavones, which are plant-derived compounds classified as phytoestrogens. Isoflavones possess a chemical structure similar to 17-beta-estradiol and can bind weakly to human estrogen receptors, particularly estrogen receptor beta. A systematic review of 15 randomized controlled trials comprising 1,952 participants found that soy-based interventions significantly reduced vasomotor symptoms compared with control groups. A clinical trial evaluating a low-fat plant-based diet incorporating whole cooked soybeans demonstrated notable reductions in moderate-to-severe hot flashes alongside improvements in quality of life.
Whole soy foods are nutritionally superior to high-dose isolated isoflavone supplements. Incorporating organic edamame, traditional tofu, fermented tempeh and unsweetened soy milk provides complete protein, minerals and fiber alongside isoflavones. Individual responses to soy foods vary based on gut microbiome composition, specifically whether an individual possesses the bacterial strains required to convert the soy isoflavone daidzein into equol, a more active metabolite.
Identifying personal symptom triggers through a short-term food and symptom log can provide practical clarity. Common dietary triggers that can provoke vasomotor episodes include:
Dietary modifications should be viewed as supportive lifestyle tools rather than guaranteed cures. When vasomotor symptoms cause severe sleep deprivation or impair daily functioning, discuss evidence-based medical treatments with a qualified healthcare provider.
Sustainable weight management after menopause is built on consistent nutritional composition rather than aggressive calorie deficits. Chronic undereating causes muscle loss, lowers thyroid hormone conversion, elevates cortisol and triggers intense compensatory hunger. Building a balanced plate around protein, fiber and quality fats creates satiety, maintains stable blood sugar and fuels daily movement.
The strength-supporting plate framework simplifies meal preparation without requiring tedious calorie counting or restrictive food eliminations. This visual model can be adapted to any cultural preference, schedule or culinary background.
To implement this model successfully, consider these adaptable daily frameworks designed for different lifestyles and practical needs.
Some postmenopausal women experience reduced appetite due to medication side effects, stress or lower activity levels. Undereating leads to muscle wasting and micronutrient shortfalls. When appetite is low, focus on nutrient-dense, easily digested meals:
Nutritious eating does not require specialty items or expensive superfood supplements. Staple pantry goods offer exceptional nutritional value:
To broaden your practical approach to midlife wellness, read through our extensive library of nutritional guidance resources.
General nutrition advice provides a helpful baseline, but individual health status determines specific dietary parameters. Midlife women often manage overlapping health considerations, including hypertension, subclinical hypothyroidism, metabolic syndrome and gastrointestinal sensitivities. Personalizing your approach ensures safety and effectiveness.
Certain clinical situations require formal medical evaluation and tailored medical nutrition therapy rather than generic self-directed changes:
Any vaginal bleeding or spotting occurring more than 12 months after your final period is abnormal and requires prompt gynecological assessment. If iron deficiency is identified, do not simply take iron pills. Your clinician must evaluate the gastrointestinal tract and reproductive system to identify any source of occult blood loss.
If a DEXA bone density scan reveals osteoporosis, nutrition forms one supportive component of care. Bone-directed pharmaceutical treatments, fall prevention strategies and supervised physical therapy may be required to prevent debilitating hip or spinal fractures.
Women with impaired renal function cannot process excessive protein loads without straining remaining nephrons. If your estimated glomerular filtration rate is reduced, work directly with a nephrologist and registered dietitian to establish safe, individualized daily protein limits.
Marked elevations in fasting glucose, hemoglobin A1c, triglycerides or Apolipoprotein B warrant targeted nutritional adjustments paired with medical monitoring. Dietary modifications should complement, rather than arbitrarily replace, prescribed cardiometabolic medications.
For more details on our evidence standards and clinical perspectives, please explore Refemina's editorial philosophy.
Midlife women are frequently targeted by commercial marketing campaigns promoting unverified supplements, extreme detox protocols and restrictive eating plans. Maintaining an evidence-informed perspective requires recognizing where current scientific research is strong, where it is preliminary and where it is absent.
Current nutritional evidence is robust regarding the benefits of progressive resistance training, adequate dietary protein, Mediterranean-style dietary patterns and calcium-rich foods. These foundational strategies consistently improve muscular, skeletal and cardiovascular outcomes in postmenopausal populations.
Evidence remains limited or mixed in several heavily marketed areas:
While whole soy foods show moderate benefits for vasomotor symptoms, clinical trial results for concentrated isoflavone pills and herbal extracts like black cohosh or red clover are heterogeneous. Study outcomes vary widely based on extraction methods, dosages and participant microbiome profiles.
No single food, seed cycling routine or green powder can restore ovarian estrogen production after menopause. Diet supports metabolic adaptation to hormonal shifts, but it does not reproduce premenopausal hormone levels.
Compounds such as collagen peptides, resveratrol and high-dose antioxidants are frequently promoted as essential postmenopausal therapies. Long-term randomized controlled trials proving that these supplements prevent clinical fractures, halt vascular aging or build lean muscle independently of exercise are lacking.
Approaching midlife nutrition with curiosity, patience and critical thinking protects you from unnecessary financial expense and nutritional frustration. Focus your energy on sustainable whole-food patterns and regular strength training.
Intermittent fasting, such as a 16:8 time-restricted feeding schedule, is a personal scheduling preference rather than a metabolic requirement. Fasting can help some women manage total caloric intake without counting calories. However, compressed eating windows can make it difficult to consume adequate protein, fiber and calcium across the day. If fasting causes low energy, poor workout performance or disordered eating thoughts, prioritize regular meals.
Hormone replacement therapy effectively treats vasomotor symptoms, reduces bone loss and helps manage genitourinary symptoms. However, hormone therapy is not a weight loss medication or a replacement for wholesome nutrition. Clinical position statements confirm that hormone therapy has little effect on long-term weight trajectories. Nutrition and exercise provide foundational cardiometabolic and muscular benefits that hormone therapy cannot duplicate.
No. Severely restricting carbohydrates is unnecessary for midlife fat loss and can compromise dietary fiber intake, thyroid function and workout performance. The key is carbohydrate quality. Prioritize fiber-rich, minimally processed carbohydrates such as oats, legumes, berries, sweet potatoes and whole grains while reducing refined sugars, sugary beverages and processed snack foods.
Current scientific research does not support the claim that dairy products cause systemic inflammation in individuals without milk allergies or lactose intolerance. Minimally processed dairy foods like plain Greek yogurt, kefir and cottage cheese provide high-quality protein, bioavailable calcium and beneficial probiotics that support bone density and gut health. If you prefer not to consume dairy, fortified soy products provide an excellent nutritional alternative.
Nutrition after menopause is not about shrinking your body through restrictive deprivation; it is about providing the deliberate fuel, protein and minerals necessary to sustain physical strength, cardiovascular health and active independence for the decades ahead.

Follow Refemina for research-led resources on hormonal change, strength, metabolism, nutrition, skin, intimate wellbeing and confidence through midlife.


Keep learning about the changes that shape energy, strength, confidence and wellbeing through midlife.
Explore Resources

